Dr. Ahmed Farhan
Medical Disclaimer: This article is for educational and informational purposes only and does not constitute individual medical advice, diagnosis, or clinical treatment. Always consult your personal physician or qualified healthcare provider regarding medical conditions, prescription changes, or new health regimens.
Transparency Disclosure: Dibesity features independent, evidence-based medical research. Some articles may contain vetted affiliate links to metabolic wellness products; if you make a purchase, we may earn a modest commission at no extra cost to you.
There is no single list of foods to avoid that suits every person with diabetes and kidney disease. The best choices depend on your kidney function, urine albumin level, blood potassium and phosphorus, blood pressure, medicines, and glucose control.
In general, people are advised to limit sodium and ultra-processed foods. Many are also advised to watch potassium and phosphorus if blood tests show a problem, and to set a protein target with their care team rather than cutting protein out. This article explains what the evidence supports and where it is uncertain.
What is diabetic kidney disease (DKD)?
Diabetic kidney disease is chronic kidney disease (CKD) caused by diabetes. It is a leading cause of kidney failure worldwide and often causes no symptoms for years.
Older terms such as “diabetic nephropathy,” “microalbuminuria,” and “macroalbuminuria” are now generally replaced by DKD and standardized albuminuria categories.
Current practice classifies CKD by two measurements:
- eGFR (G1 to G5): how well the kidneys filter blood.
- Urine albumin-to-creatinine ratio, ACR (A1 to A3): how much albumin leaks into the urine.
| Albuminuria category | Urine ACR (mg/g) | Meaning |
|---|---|---|
| A1 | Below 30 | Normal to mildly increased |
| A2 | 30 to 300 | Moderately increased (formerly “microalbuminuria”) |
| A3 | Above 300 | Severely increased (formerly “macroalbuminuria”) |
Persistently high blood glucose and high blood pressure damage the kidney’s tiny filtering units. Over time, albumin leaks into the urine and filtration declines. Swelling of the legs or around the eyes and foamy urine can appear later, but regular blood and urine testing is how DKD is detected early.
Who is at higher risk?
- Long-standing or poorly controlled diabetes
- High blood pressure
- Smoking
- Obesity and physical inactivity
- Cardiovascular disease
- High salt intake
- Regular use of NSAID pain relievers, which can harm kidney function
Not everyone with diabetes develops kidney disease.
Can diet slow DKD? What the evidence shows
Diet is one part of care alongside glucose control, blood pressure control, and kidney-protective medicines.
Diet cannot be assumed to reverse established DKD. The best-supported aim is to slow progression and reduce complications. Remission or cure is not established by the evidence reviewed here.
Protein: the target matters more than avoidance
A 2023 Cochrane review of eight trials (486 adults with DKD not on dialysis) compared low-protein diets (0.6 to 0.8 g/kg/day) with usual intake (1.0 g/kg/day or more). It found the following (PMID 36594428):
- Low-certainty evidence that a low-protein diet may make little or no difference to death or progression to kidney failure.
- Very low-certainty evidence, so uncertain effects on the yearly decline in kidney filtration.
- Poor adherence in nearly half of the studies. Malnutrition was not seen in seven studies, but one noted it in the low-protein group.
- Most trials had high or unclear risk of bias and were small.
In practice, the protein target should be individualized by stage, nutritional status, and whether you are on dialysis.
People on dialysis generally need more protein than those not on dialysis because dialysis removes protein.
The specific g/kg figures in the original article (0.8 g/kg for early stages, 0.6 g/kg for stage 3 or above) should be verified against current KDIGO and ADA guidance before use. Do not restrict protein on your own.
Ketoanalogue supplements: a specialist-supervised option
Ketoanalogues are prescribed supplements sometimes added to a low-protein diet. A systematic review of 11 studies in non-dialysis DKD concluded that supplemented low-protein diets could be considered effective and safe, but larger studies are needed (PMID 35276799).
A randomized trial of 149 adults with type 2 diabetes and CKD stages 3b to 4 gave all participants 0.6 g/kg/day of protein for one year.
The group receiving ketoanalogues had a smaller decline in cystatin C-based eGFR (about -4.3 versus -8.5 mL/min).
There was no difference in creatinine-based eGFR. The authors noted the small sample, short follow-up, and possible changes in creatinine metabolism, and called for confirmation (PMID 42654210).
These products should only be used under nephrology supervision. Do not buy them over the counter on the basis of this evidence.
Sodium: the best-supported restriction
A meta-analysis of 12 randomized trials in DKD with albuminuria found that sodium restriction lowered systolic blood pressure by about 4.7 mmHg and diastolic by about 2.3 mmHg.
It also reduced urinary albumin excretion, especially in macroalbuminuria. The authors described the benefit as coming from moderate sodium restriction (PMID 34671892).
The outcomes were blood pressure and albuminuria, not kidney failure or survival. The original article’s sodium categories, including “extreme” restriction below 1,000 mg/day, were not supported by this analysis, so your clinician should set your target.
For practical ideas, see these low-sodium breakfast options.
Overall dietary pattern
Eating patterns may matter more than single nutrients, but the evidence is mixed.
- Mediterranean diet: A systematic review of six mostly observational studies found that higher adherence was generally associated with lower risk of developing diabetic nephropathy. Associations ranged from 21% to 86%, two studies found no significant association, and the authors said causation and effects on progression cannot be concluded (PMID 42508971).
- In the CORDIOPREV secondary analysis (1,002 people with coronary heart disease), a Mediterranean diet was associated with less eGFR decline and lower urine albumin than a low-fat diet. This was seen only in the subgroup with both type 2 diabetes and obesity (PMID 38755195). It was a secondary analysis, so the finding is exploratory.
- Ultra-processed foods: A meta-analysis of 14 cohort studies found higher intake was associated with more incident diabetes (very low-certainty evidence). Preliminary data from four cohorts suggested possible links to CKD in people with diabetes (PMID 39848440). These are observational associations, not proof of cause.
A Mediterranean-style pattern emphasizes vegetables, legumes, fish, olive oil, and whole grains. Because some of these foods contain potassium and phosphorus, it may need adjusting for advanced CKD.
See Dibesity’s overview of nutrition for obesity and diabetes.
Foods and drinks people with DKD are often asked to limit
The table below lists common concerns. Whether each applies to you depends on your lab results. None of the food lists below were validated by the studies cited in this article. They reflect standard renal dietitian practice and should be confirmed with your care team.
| Concern | Why it matters | Foods often reviewed with a dietitian |
|---|---|---|
| Sodium | Raises blood pressure and urine albumin | Processed and cured meats, canned soups, instant noodles, salty snacks, fast food, soy and other sauces |
| Potassium (only if blood levels are high or at risk) | Kidneys may clear potassium poorly, and some medicines raise it further | Oranges and orange juice, bananas, dates and other dried fruit, potatoes, tomatoes, pomegranate juice, and salt substitutes made with potassium chloride |
| Phosphorus (if blood levels are high) | Excretion falls as kidney function declines | Dark colas and other drinks with phosphate additives, processed foods with “phos” ingredients, and some dairy products. See yogurt types compared. |
| Refined sugars and rapidly absorbed carbohydrates | Worsen glucose control | Sugary drinks, sweets, fruit juices, large portions of white bread, white rice, and pastries |
| Excess protein, especially processed meat | Protein targets are individualized | Large portions of red and processed meat. See high-protein diets and the kidneys. |
Some details in the original article need correcting or flagging:
- It listed apricots and pomegranate juice as safe, and used both in a sample plan alongside skim milk. These are potassium-containing foods that may not suit people with high potassium.
- The 800 to 1,000 mg/day phosphorus limit, the “50% vegetable phosphorus absorption” figure, and the calcium limit lacked cited support and have been removed. Phosphorus added to processed foods is generally absorbed more readily than phosphorus naturally present in foods, but your dietitian should guide specifics.
- Low-glycemic-index claims (such as a GI under 55 and generic “cereals”) and fiber targets attributed to the FDA could not be verified. Fiber from vegetables, legumes, and whole grains is generally encouraged, but choices may need adjusting for potassium and phosphorus.
- The claim that higher PUFA intake lowers kidney failure risk had no supporting citation, so it has been removed. Replacing saturated and trans fats with unsaturated fats such as olive oil is a general heart-health principle. The ideal fat intake in DKD is not established.
Fruit and vegetables: don’t cut them out unnecessarily
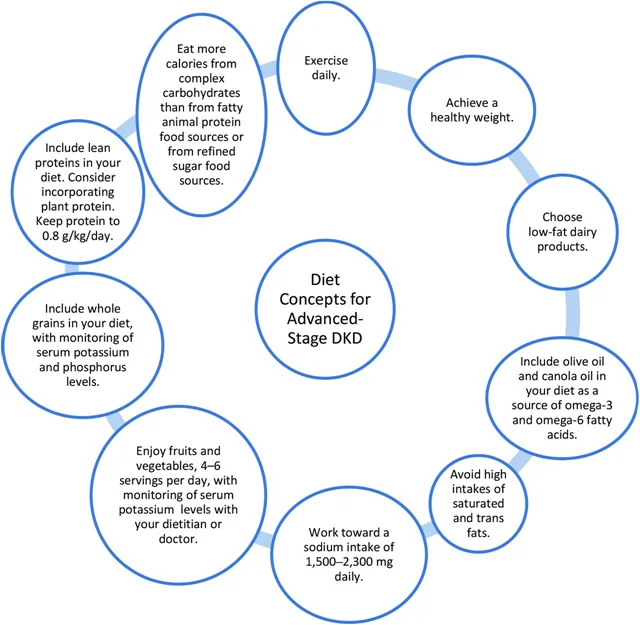
Fruit and vegetables protect the heart and support weight and glucose control. Unless your potassium is high, you do not necessarily need to avoid them.
Lower-potassium choices often suggested include apples, berries such as strawberries, grapes, and pears, and vegetables such as cauliflower, cabbage, cucumber, and carrots. Portion size matters.
Canned fruit in syrup adds sugar, and canned vegetables are often high in sodium. Rinsing canned vegetables helps reduce sodium.
Glucose targets and safety
- Glycemic targets should be individualized. The original article gave a universal HbA1c target below 7%. In CKD, targets may be adjusted for hypoglycemia risk, age, and other conditions, and HbA1c can be less reliable in advanced CKD.
- Glucose spills into the urine above a “renal threshold.” It is often cited as around 180 mg/dL, not the 250 mg/dL stated originally, and it varies between people.
- Reduced kidney function lengthens the action of insulin and some diabetes drugs, which can raise hypoglycemia risk. Learn to recognize hyperglycemia and hypoglycemia, and coordinate meals with medicines.
Medicines that matter alongside diet
Diet works together with medical treatment. The original article omitted current kidney-protective therapies. Diabetes-in-CKD guidance from ADA and KDIGO discusses several, and the reviewing physician should check current recommendations and your suitability:
- RAAS blockers (ACE inhibitors or ARBs): used for blood pressure and albuminuria. They can raise potassium and need blood tests after starting or changing dose.
- SGLT2 inhibitors: considered in many people with diabetes and CKD. Possible adverse effects include genital infections and volume depletion, and rarely ketoacidosis.
- Finerenone: a non-steroidal mineralocorticoid receptor antagonist considered for selected people with albuminuria. It can raise potassium.
- Metformin and other glucose-lowering drugs may need dose adjustment or discontinuation depending on eGFR.
Because several of these medicines raise potassium, dietary potassium advice should be based on your current blood tests and not applied generically. If high potassium becomes a problem, medicines called potassium binders are sometimes used (see Lokelma vs Kayexalate).
Pain relievers and nephrotoxic drugs
NSAIDs (such as ibuprofen and naproxen) and COX-2 inhibitors can reduce kidney blood flow and should generally be avoided in DKD unless a clinician advises otherwise.
Paracetamol (acetaminophen) and topical treatments are commonly used instead. Other options such as pregabalin, tramadol, and codeine require kidney-function dose adjustment and carry their own risks, so they should only be used under medical supervision.
Supplements and herbal products
The original page promoted berberine, powders, and other supplements. No studies cited here support these products for DKD.
Berberine and other supplements may interact with medicines, can cause hypoglycemia alongside diabetes treatment, and some herbal products are harmful in CKD.
Supplements never replace prescribed treatment. Check with your clinician or pharmacist before using any.
Ask your nephrologist for a referral to a registered dietitian experienced in kidney disease and diabetes. For general principles, see the ADA diabetic diet recommendations, the American Heart Association diet, and guidance on medical nutrition therapy.
Practical tips
- Read food labels for sodium, and for “phos” additives and potassium chloride.
- Cook from fresh ingredients more often than packaged or fast foods.
- Keep carbohydrate portions fairly consistent across meals.
- Be physically active as advised by your clinician, and aim for a healthy weight.
- Do not smoke.
- Get urine ACR, eGFR, potassium, and HbA1c checked regularly.
- Bring all medicines and supplements to appointments.
- Dialysis and advanced CKD need separate dietary plans from specialists.
Frequently asked questions
Do I have to stop eating protein if I have diabetes and kidney disease?
No. Protein is essential. The evidence for strict restriction is uncertain, so your target should be set with your care team, with attention to avoiding malnutrition.
Which fruit should I avoid?
It depends on your potassium level and medicines. High-potassium fruits such as oranges, bananas, and dried fruit are commonly limited if potassium is high. Many other fruits are acceptable in sensible portions.
Is a Mediterranean diet good for diabetic kidney disease?
It may be associated with lower risk of developing DKD, but the evidence is mostly observational and cannot show cause. It may need adjusting for potassium and phosphorus in advanced CKD.
Can diet cure diabetic kidney disease?
Diet, glucose and blood pressure control, and medicines can slow progression. A cure or remission of established DKD has not been shown in the evidence reviewed here.
Conclusion
The safest approach is an individualized one. It limits sodium and ultra-processed foods, adjusts potassium and phosphorus according to blood tests, sets a protein target with a dietitian, and combines diet with kidney-protective medicines.
Much of the dietary evidence in DKD is low-certainty, observational, or from small trials, so personalized supervision matters more than generic food lists.
References
- Jiang S, Fang J, Li W. Protein restriction for diabetic kidney disease. Cochrane Database Syst Rev. 2023. PMID 36594428
- Bellizzi V, et al. Ketoanalogue supplementation in patients with non-dialysis diabetic kidney disease: a systematic review and meta-analysis. Nutrients. 2022. PMID 35276799
- Paniagua R, et al. Low-protein diet supplemented with ketoanalogues and progression of chronic kidney disease in diabetic patients: a multicenter randomized controlled trial. Nutrients. 2026. PMID 42654210
- Chen Y, et al. Effect of a sodium restriction diet on albuminuria and blood pressure in diabetic kidney disease patients: a meta-analysis. Int Urol Nephrol. 2022. PMID 34671892
- Sykaras I, et al. Adherence to the Mediterranean diet and its effects on the onset and progression of diabetic nephropathy: a systematic review. Ren Fail. 2026. PMID 42508971
- Podadera-Herreros A, et al. Mediterranean diet as a strategy for preserving kidney function in patients with coronary heart disease with type 2 diabetes and obesity: a secondary analysis of CORDIOPREV. Nutr Diabetes. 2024. PMID 38755195
- Souza M, et al. Association between higher consumption of ultra-processed foods and risk of diabetes and its complications: a systematic review and updated meta-analysis. Metabolism. 2025. PMID 39848440
This draft is for educational purposes only. It is not a substitute for personal medical advice, diagnosis, or treatment.
Recommended Metabolic Health & Wellness Products
A curated index of metabolic support compounds, prebiotic fibres, functional botanicals, and zero-sugar pantry staples selected for ingredient quality and scientific relevance.
Transparency Notice: As an Amazon Associate, Dibesity.com earns from qualifying purchases made through external affiliate links, at no extra cost to you.
Targeted Metabolic & Cellular Support
Apigenin Powder
A bioflavonoid compound explored for cellular protection, circadian rhythm support, and metabolic balance.
View on Amazon →97% Pure Berberine Powder (100 g)
High-purity berberine HCl powder for customizable serving sizes and metabolic pathway support.
View on Amazon →Berberine Powder (200 g)
Bulk berberine powder formulation. Check the listing for ingredient details, certificates of analysis, and reviews.
View on Amazon →Pure Inositol Powder
Pure Myo-Inositol and D-Chiro-Inositol powder formulation for metabolic and reproductive wellness. Check the listing for details.
View on Amazon →Functional Botanicals & Prebiotic Fibres
Psyllium Husk with Fennel & Cardamom
A soluble prebiotic fibre blend with warming digestive spices to support gut motility and postprandial glucose moderation.
View on Amazon →100% Pure Hibiscus Powder
Anthocyanin-rich botanical powder supporting cardiometabolic markers, nitric oxide pathways, and vascular health.
View on Amazon →Roasted Barley Powder
A roasted whole-grain grain alternative suitable for nutritious, caffeine-free herbal teas and warm beverages.
View on Amazon →Allulose Confectionery (Low-Glycaemic)
Strawberry Allulose Gummies
Low-calorie, rare-sugar allulose gummies designed to satisfy sweet cravings without causing glycemic spikes.
View on Amazon →Watermelon Allulose Gummies
Refreshing watermelon flavour sweetened with keto-compatible allulose. Minimal net impact on blood sugar.
View on Amazon →Mixed Berry Allulose Gummies
Berry-flavoured chewable treats sweetened with rare sugar allulose for a clean, tooth-friendly profile.
View on Amazon →